They knew heart attacks happen. Nobody knew what to do.
Cardiocare was a Philips concept for Indian adults over 30. My job: turn a far-away heart risk into something people act on daily.
Problem
The gap was the next action.
Prevention has no natural trigger, so the question was where to step in. A 141-source literature review mapped the risk drivers of coronary artery disease.
What I found
Few knew their own risks. None had a next action.
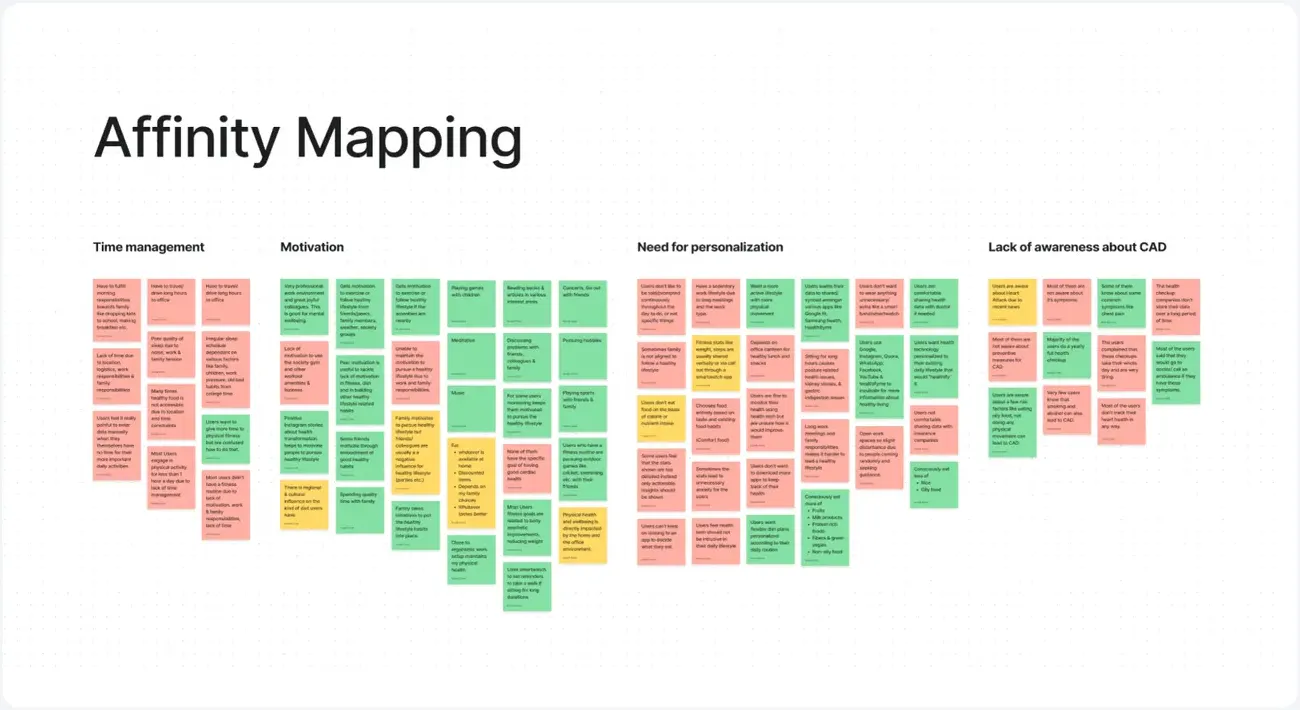
I ran 18 semi-structured interviews about daily routines and coded them into four themes: no time, low motivation, a need for personalization, little awareness.
What it cost
It holds for working adults; people in cardiac care, and clinicians, are still untested.
See the affinity map
- Most didn’t know the symptoms or the steps that prevent an attack.
- Each theme got an answer: Learn for awareness, Routine for time and personalization, the wearable and WhatsApp for motivation.
- The new brief: one next action inside a routine people already have.

What I decided
I chose a system.
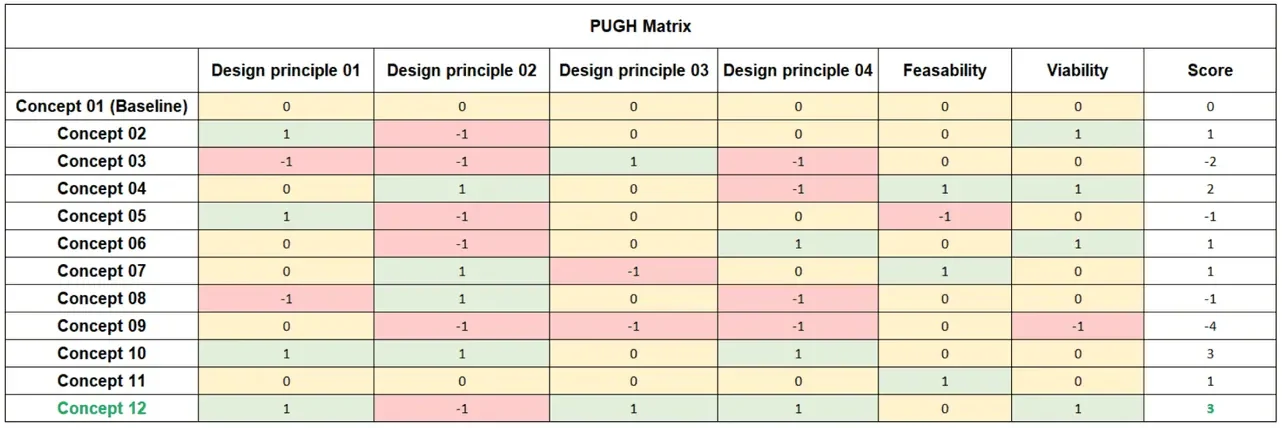
SCAMPER opened directions from a single tracker to a full ecosystem. I scored the feasible ones in a Pugh matrix on four design principles, feasibility, and viability.
What it cost
We wrote the criteria ourselves, so the matrix reduced bias but didn’t remove judgment.
Proof
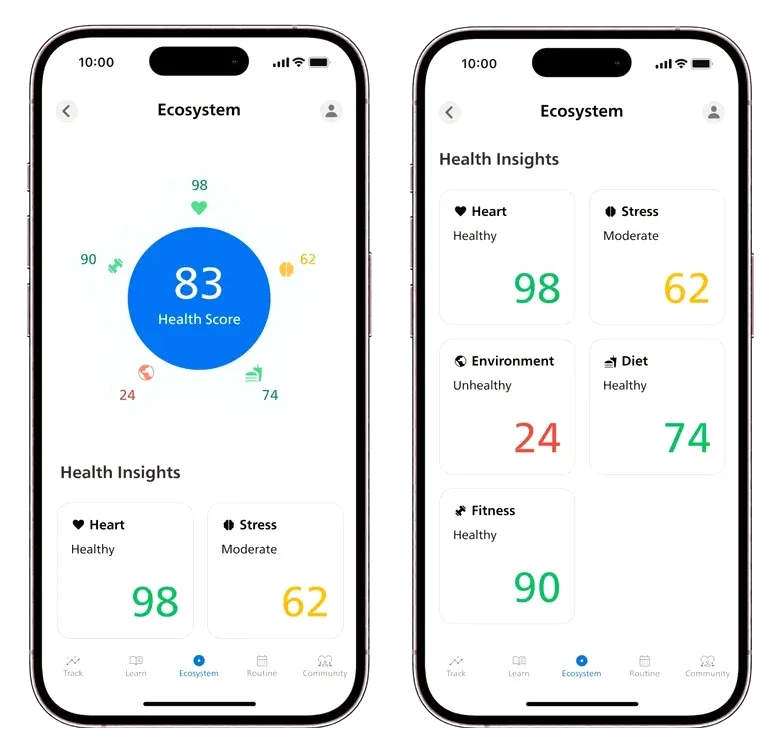
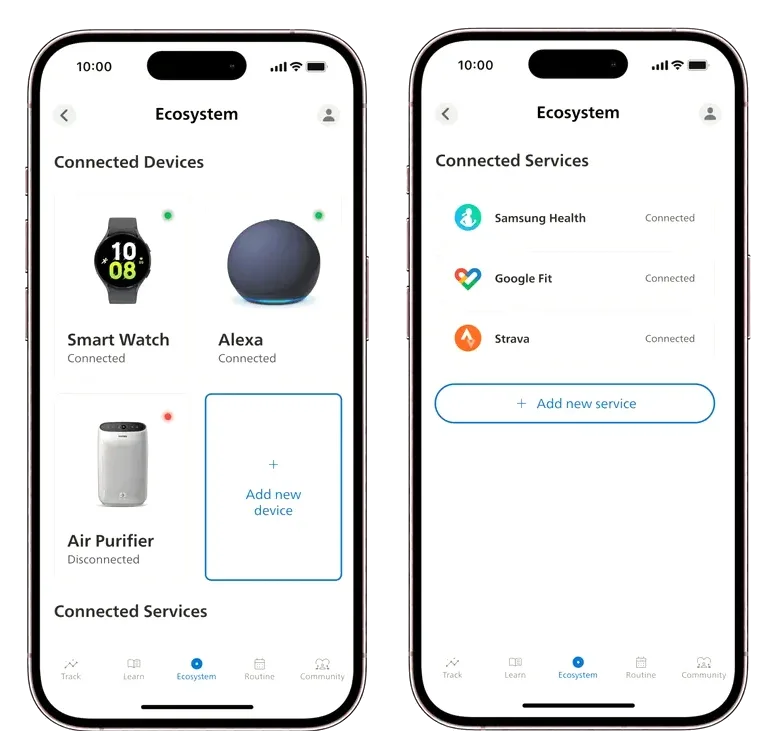
It won the tie: learning, routines, tracking, guidance, devices and WhatsApp in one service.
See the principles and the matrix
- Minimum intrusion for maximum motivation
- Involve major influencers for frictionless adoption of healthy habits
- Continuous guidance for heart‑healthy living
- Personalization for integration and sustainable habit formation
What I tested
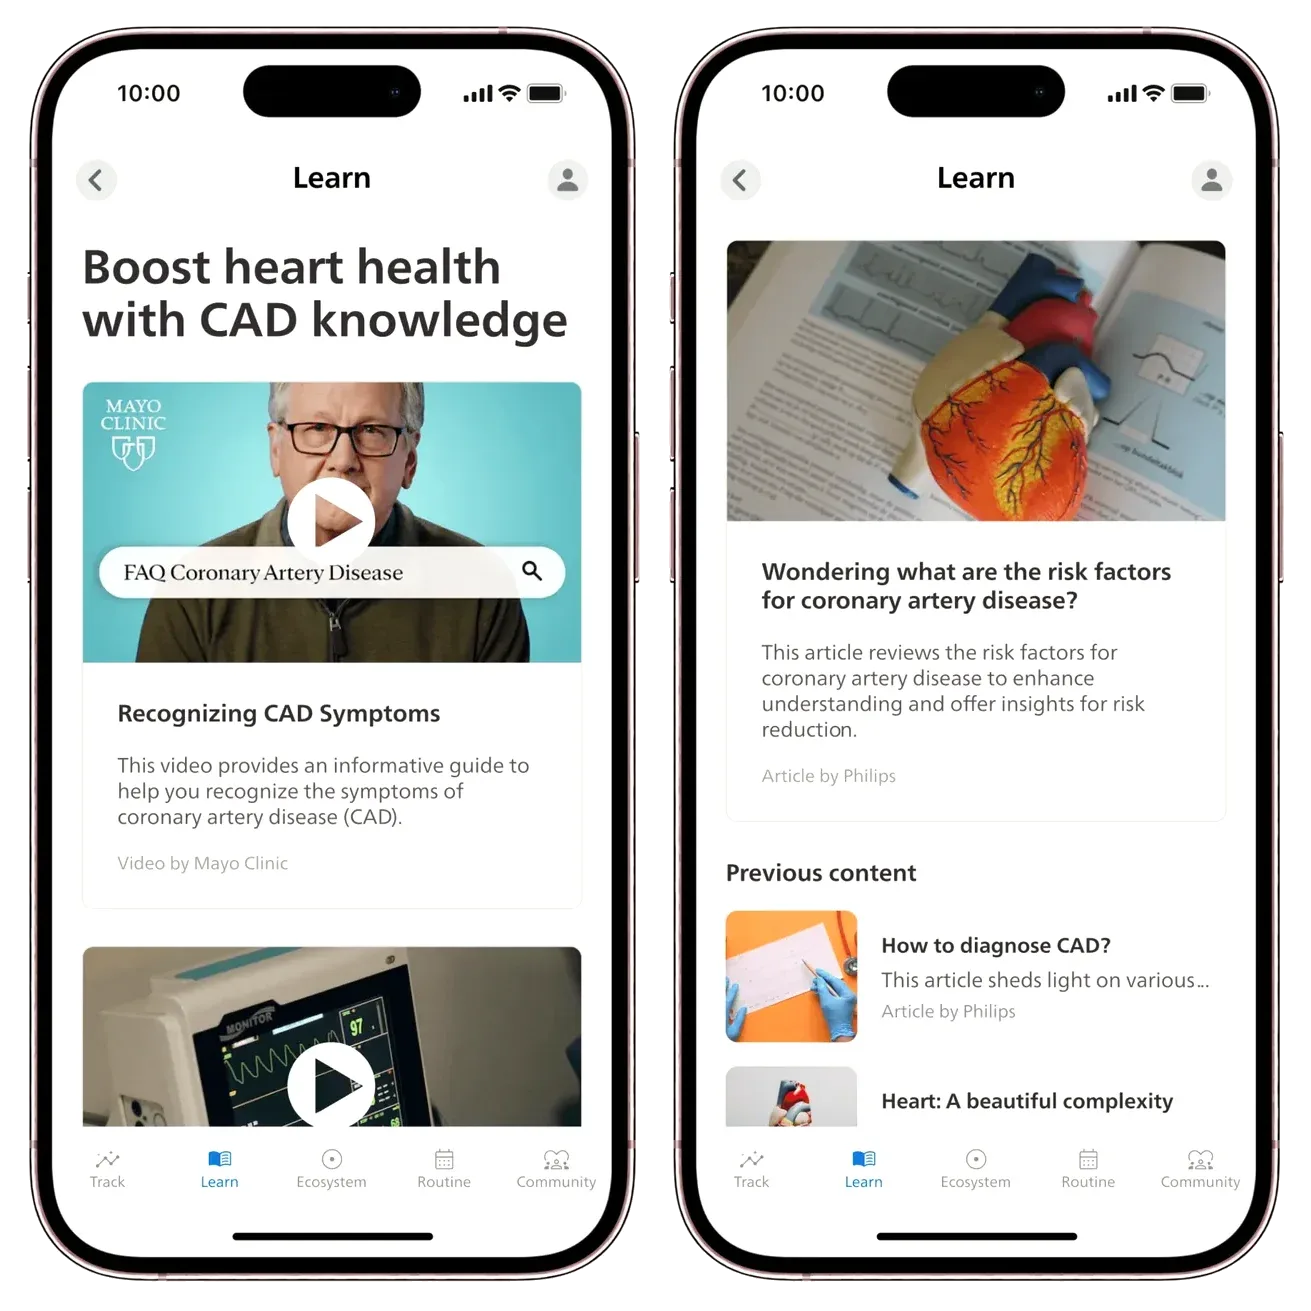
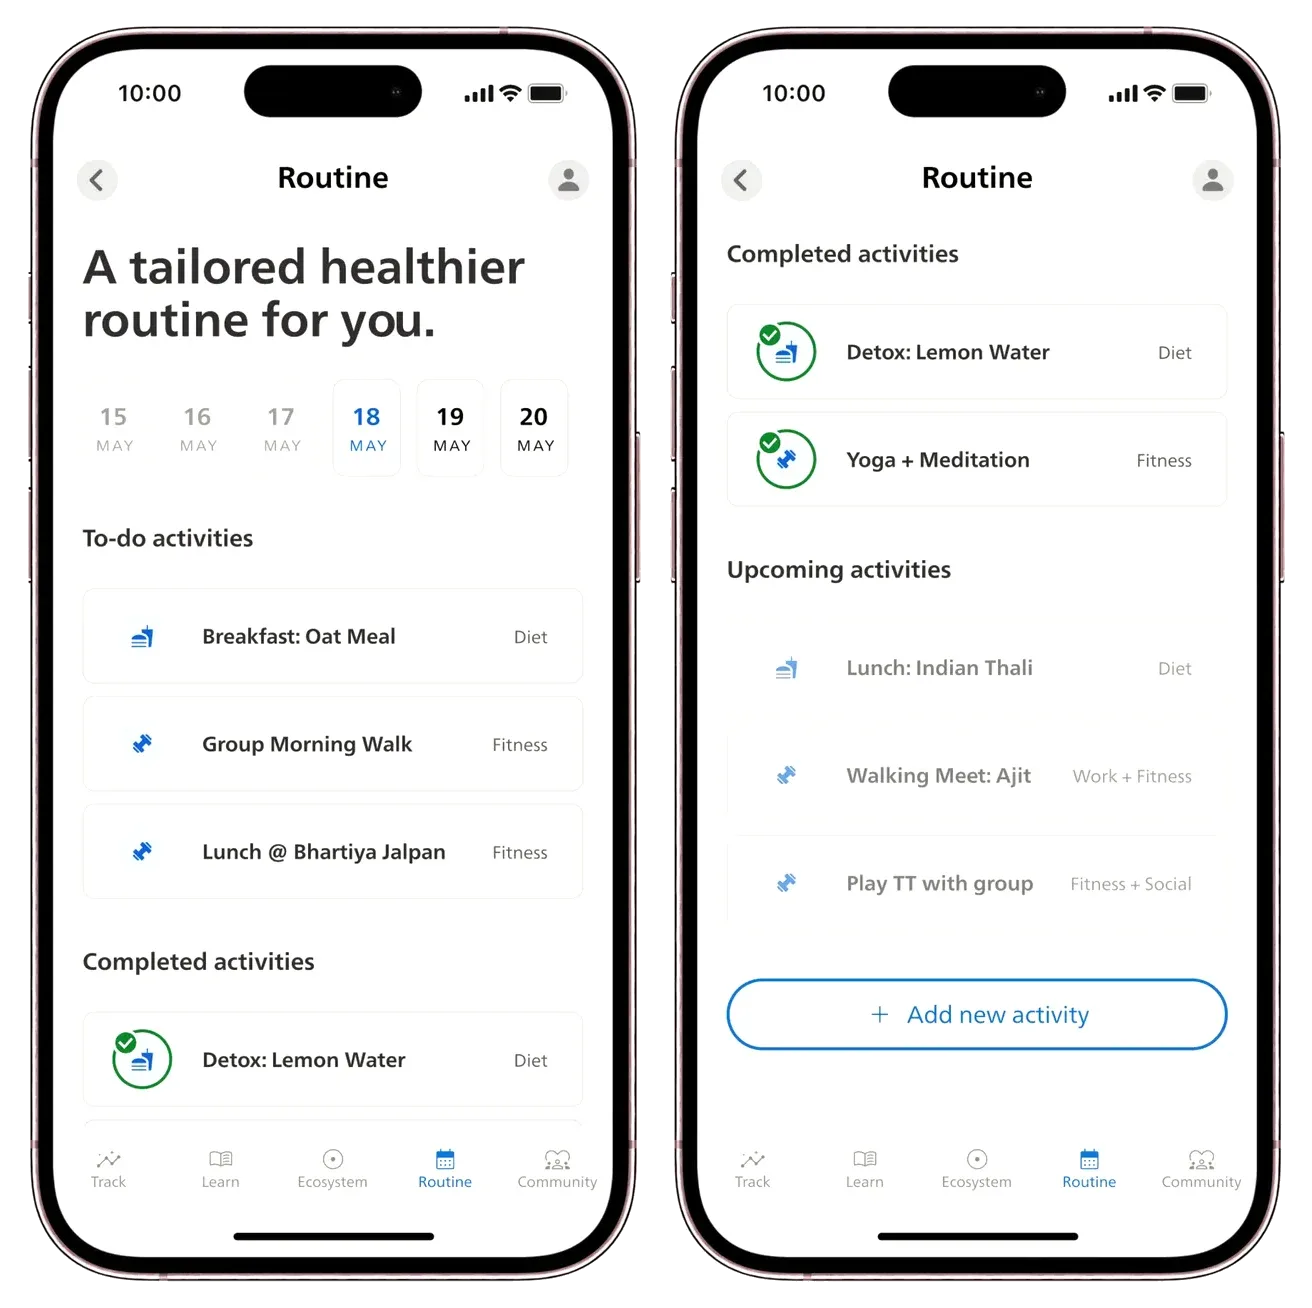
Learn explains the risk. Routine sets today’s action.
Moderated prototype sessions tested connect, learn, act: could people find their next action without help? The team concept went on to win an iF Design Award in 2024.
My accessibility gap
- Connect: the wearable syncs steps, stress, and heart rate; WhatsApp pulls you back.
- Learn: a Mayo Clinic video and articles; Health Wiz answers in plain language.
- Act: Routine turns the risk and the learning into a weekly plan for that person.
The intended users included adults over 30 with heart risk, but the accessibility claim came from using the Philips design system rather than testing the experience with people at the edges.
Until they test it, I can claim the design system’s conformance, not accessibility.
Looking back
Next, I set the target before testing.
Next time I’d agree the target and minimum sample before testing, watch task success beside the survey, and ask for consent once for each data source the app connects.
Beyond the brief
Nobody had scoped interviews, so I wrote the objectives, recruited people, and ran them myself.